

Ending River Blindness in Kaduna Means Reaching Those Left Behind
Related Stories




At a recent policy dialogue on river blindness, held in Kaduna and convened by Nigeria Health Watch and the Kaduna State Ministry of Health, a local government Neglected Tropical Disease (NTD) officer described a familiar problem. Community drug distributors (CDDs) arrive during the farming season, when some residents are away working. People who might willingly take treatment miss the visit. Unless someone returns, an awareness message will do little to change that outcome.
The policy dialogue was held as part of the Bridging Borders, Breaking Blindness project, funded by the Global Institute for Disease Elimination (GLIDE). The discussion raised a practical question. Before asking why people are not participating, have programmes made it possible for them to do so?

River blindness, or onchocerciasis, is caused by a parasite transmitted through bites from infected blackflies, which breed in fast-flowing rivers. It can cause severe itching, skin disease and permanent blindness. Regular treatment with ivermectin helps prevent these consequences and interrupt transmission.
In communities targeted for mass treatment, eligible residents include adults and children who meet the minimum size requirement, at least 90 cm tall, roughly equivalent to 15 kg, as well as those without symptoms.
Under WHO guidance, pregnant women, breastfeeding mothers in the first week after childbirth, and people who are seriously ill are excluded from routine campaign treatment. Programmes must continue reaching eligible residents over many years.
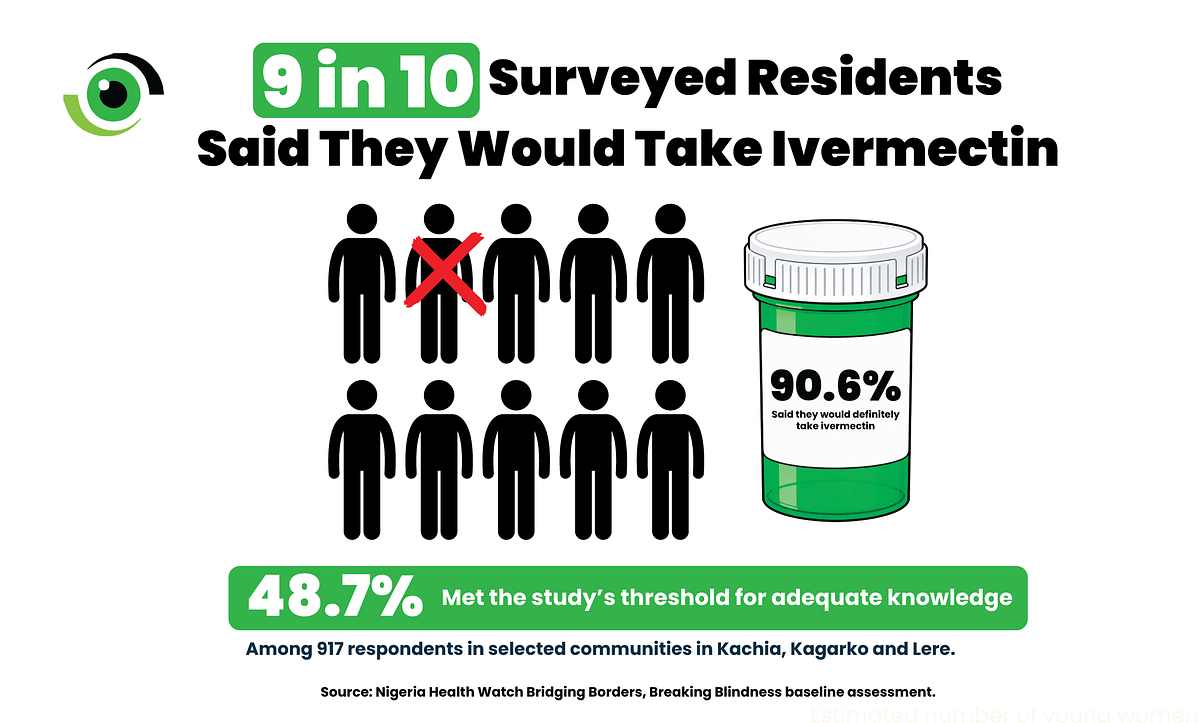
The project’s 2026 baseline assessment identifies the gap and offers some encouragement. Among 917 respondents in selected communities in Kachia, Kagarko and Lere, 48.7% met the study’s threshold for adequate knowledge, while 90.6% said they would definitely take ivermectin. These findings challenge the assumption that greater awareness will, by itself, solve the problem of poor participation, as willingness to take treatment far exceeded levels of knowledge.
Campaign teams also need to establish whether medicines and distributors reach the people expected to take them. Dr Sadiq Abubakar, Director of Public Health at the Kaduna State Ministry of Health, put the consequences plainly, “behind every untreated eligible person is a community that will still remain at risk.”
For Kaduna, rebuilding participation involves explaining why treatment is needed again. After nearly three decades of annual ivermectin distribution, post-treatment assessments showed that transmission had been interrupted, and federal and state health authorities and partners approved the decision to stop mass treatment in 2018.
However, following assessments as well as research published in August 2025 detected transmission in Kachia and Kagarko. The researchers discussed migration, insecurity and differences in diagnostic sensitivity, without establishing a single cause.
Residents deserve a clear explanation of what changed, what the evidence shows and why eligible people who feel well still need treatment. Programme managers should agree on distribution dates with communities, plan return visits, and provide a place for people to ask questions about the medicines. Women, farmers, people with disabilities and displaced households should help shape those arrangements.
Traditional leaders, imams, and church leaders can identify households that are being missed and raise concerns with health officials before the next round. Rebecca Martin, a representative of a community-based advocacy hub, described how residents help shape its work, “We don’t just go into the community and tell them what we have, but we allow them to tell us what they know about river blindness and how it is caused and prevented.”
Sustaining progress against neglected tropical diseases (NTDs) will require stronger domestic financing and greater government ownership. External partner funding can help accelerate programmes, but it cannot substitute for predictable government resources to finance the routine costs of reaching communities. The draft communiqué from the dialogue therefore proposes a dedicated provision for NTDs in Kaduna’s 2027 budget, alongside contributions from local governments. For this commitment to translate into action, the allocation must be backed by clear costing, defined responsibilities and timely release of funds.
Domestic financing is also essential to ensuring that the people responsible for delivering treatment are adequately supported. The discussion about unpaid allowances highlighted the need for transparent payment systems, with agencies verifying outstanding claims and making agreed rates and payment timelines clear. Drug distributors need training, supervision and the resources to travel between settlements. Relying on volunteers to absorb these costs themselves makes sustained and equitable treatment coverage difficult.
“We have been waiting for integration for the past 20 years,”said Anita Gwom, Programme Director, NTDs, at Sightsavers Nigeria. The draft communiqué proposes NTD focal persons in primary healthcare facilities, staff training and routine supervision. These measures would give residents a place to report a missed visit or seek help between campaigns, provided staff have clear responsibilities and access to treatment or referral services. State and local government teams should explain how a complaint made at a health centre will lead to follow-up in the community.
Kaduna also needs dependable funding to establish when treatment can safely end. Under the World Health Organization (WHO)’s stopping treatment guidance, decisions are based on blackfly testing and antibody testing in children and are reviewed by an independent national expert committee. Surveillance then continues for three to five years after treatment stops. Routine reports from health facilities can flag concerns, but cannot replace those assessments. Stopping treatment in a defined transmission area is also different from the WHO verifying elimination across a country.
The cost of gathering this evidence deserves attention in the 2027 budget discussions. In the Kaduna study, financial constraints meant that only 1,502 of 3,107 collected blood samples from children were analysed. Researchers cited naira devaluation, inflation and the high cost of reagents. Funding must cover laboratory work, follow-up, and field visits. Federal and state authorities, with their partners, should publish assessment methods, findings and the reasons for treatment decisions, and explain the implications to affected communities. Neighbouring states should also coordinate surveillance at points where people and blackflies cross borders.
Before the next treatment round, the state and participating LGAs should publish the agreed actions, responsible institutions and funding arrangements. The subsequent review should show which missed communities were reached and which still need follow-up.
For the farmer who missed treatment, the answer begins with a return visit at a time agreed with the community, from a distributor equipped for the visit, with transport costs and agreed allowances covered. Kaduna’s next treatment round should show whether the dialogue has changed that experience.
Leave a Comment
Your email address will not be published. Required fields are marked *